WO2016114761A1 - Method for individualized drug therapy - Google Patents
Method for individualized drug therapy Download PDFInfo
- Publication number
- WO2016114761A1 WO2016114761A1 PCT/US2015/011148 US2015011148W WO2016114761A1 WO 2016114761 A1 WO2016114761 A1 WO 2016114761A1 US 2015011148 W US2015011148 W US 2015011148W WO 2016114761 A1 WO2016114761 A1 WO 2016114761A1
- Authority
- WO
- WIPO (PCT)
- Prior art keywords
- nsaid
- disorders
- patient
- formulation
- cox
- Prior art date
- Legal status (The legal status is an assumption and is not a legal conclusion. Google has not performed a legal analysis and makes no representation as to the accuracy of the status listed.)
- Ceased
Links
Classifications
-
- A—HUMAN NECESSITIES
- A61—MEDICAL OR VETERINARY SCIENCE; HYGIENE
- A61K—PREPARATIONS FOR MEDICAL, DENTAL OR TOILETRY PURPOSES
- A61K31/00—Medicinal preparations containing organic active ingredients
- A61K31/33—Heterocyclic compounds
- A61K31/395—Heterocyclic compounds having nitrogen as a ring hetero atom, e.g. guanethidine or rifamycins
- A61K31/41—Heterocyclic compounds having nitrogen as a ring hetero atom, e.g. guanethidine or rifamycins having five-membered rings with two or more ring hetero atoms, at least one of which being nitrogen, e.g. tetrazole
- A61K31/415—1,2-Diazoles
-
- A—HUMAN NECESSITIES
- A61—MEDICAL OR VETERINARY SCIENCE; HYGIENE
- A61K—PREPARATIONS FOR MEDICAL, DENTAL OR TOILETRY PURPOSES
- A61K31/00—Medicinal preparations containing organic active ingredients
- A61K31/33—Heterocyclic compounds
- A61K31/395—Heterocyclic compounds having nitrogen as a ring hetero atom, e.g. guanethidine or rifamycins
- A61K31/41—Heterocyclic compounds having nitrogen as a ring hetero atom, e.g. guanethidine or rifamycins having five-membered rings with two or more ring hetero atoms, at least one of which being nitrogen, e.g. tetrazole
- A61K31/415—1,2-Diazoles
- A61K31/4155—1,2-Diazoles non condensed and containing further heterocyclic rings
-
- A—HUMAN NECESSITIES
- A61—MEDICAL OR VETERINARY SCIENCE; HYGIENE
- A61K—PREPARATIONS FOR MEDICAL, DENTAL OR TOILETRY PURPOSES
- A61K31/00—Medicinal preparations containing organic active ingredients
- A61K31/33—Heterocyclic compounds
- A61K31/395—Heterocyclic compounds having nitrogen as a ring hetero atom, e.g. guanethidine or rifamycins
- A61K31/54—Heterocyclic compounds having nitrogen as a ring hetero atom, e.g. guanethidine or rifamycins having six-membered rings with at least one nitrogen and one sulfur as the ring hetero atoms, e.g. sulthiame
- A61K31/5415—Heterocyclic compounds having nitrogen as a ring hetero atom, e.g. guanethidine or rifamycins having six-membered rings with at least one nitrogen and one sulfur as the ring hetero atoms, e.g. sulthiame ortho- or peri-condensed with carbocyclic ring systems, e.g. phenothiazine, chlorpromazine, piroxicam
-
- A—HUMAN NECESSITIES
- A61—MEDICAL OR VETERINARY SCIENCE; HYGIENE
- A61K—PREPARATIONS FOR MEDICAL, DENTAL OR TOILETRY PURPOSES
- A61K31/00—Medicinal preparations containing organic active ingredients
- A61K31/60—Salicylic acid; Derivatives thereof
- A61K31/612—Salicylic acid; Derivatives thereof having the hydroxy group in position 2 esterified, e.g. salicylsulfuric acid
- A61K31/616—Salicylic acid; Derivatives thereof having the hydroxy group in position 2 esterified, e.g. salicylsulfuric acid by carboxylic acids, e.g. acetylsalicylic acid
-
- A—HUMAN NECESSITIES
- A61—MEDICAL OR VETERINARY SCIENCE; HYGIENE
- A61K—PREPARATIONS FOR MEDICAL, DENTAL OR TOILETRY PURPOSES
- A61K31/00—Medicinal preparations containing organic active ingredients
- A61K31/63—Compounds containing para-N-benzenesulfonyl-N-groups, e.g. sulfanilamide, p-nitrobenzenesulfonyl hydrazide
- A61K31/635—Compounds containing para-N-benzenesulfonyl-N-groups, e.g. sulfanilamide, p-nitrobenzenesulfonyl hydrazide having a heterocyclic ring, e.g. sulfadiazine
-
- A—HUMAN NECESSITIES
- A61—MEDICAL OR VETERINARY SCIENCE; HYGIENE
- A61K—PREPARATIONS FOR MEDICAL, DENTAL OR TOILETRY PURPOSES
- A61K45/00—Medicinal preparations containing active ingredients not provided for in groups A61K31/00 - A61K41/00
- A61K45/06—Mixtures of active ingredients without chemical characterisation, e.g. antiphlogistics and cardiaca
-
- A—HUMAN NECESSITIES
- A61—MEDICAL OR VETERINARY SCIENCE; HYGIENE
- A61K—PREPARATIONS FOR MEDICAL, DENTAL OR TOILETRY PURPOSES
- A61K9/00—Medicinal preparations characterised by special physical form
- A61K9/0012—Galenical forms characterised by the site of application
- A61K9/0053—Mouth and digestive tract, i.e. intraoral and peroral administration
-
- A—HUMAN NECESSITIES
- A61—MEDICAL OR VETERINARY SCIENCE; HYGIENE
- A61P—SPECIFIC THERAPEUTIC ACTIVITY OF CHEMICAL COMPOUNDS OR MEDICINAL PREPARATIONS
- A61P1/00—Drugs for disorders of the alimentary tract or the digestive system
-
- A—HUMAN NECESSITIES
- A61—MEDICAL OR VETERINARY SCIENCE; HYGIENE
- A61P—SPECIFIC THERAPEUTIC ACTIVITY OF CHEMICAL COMPOUNDS OR MEDICINAL PREPARATIONS
- A61P11/00—Drugs for disorders of the respiratory system
-
- A—HUMAN NECESSITIES
- A61—MEDICAL OR VETERINARY SCIENCE; HYGIENE
- A61P—SPECIFIC THERAPEUTIC ACTIVITY OF CHEMICAL COMPOUNDS OR MEDICINAL PREPARATIONS
- A61P11/00—Drugs for disorders of the respiratory system
- A61P11/02—Nasal agents, e.g. decongestants
-
- A—HUMAN NECESSITIES
- A61—MEDICAL OR VETERINARY SCIENCE; HYGIENE
- A61P—SPECIFIC THERAPEUTIC ACTIVITY OF CHEMICAL COMPOUNDS OR MEDICINAL PREPARATIONS
- A61P13/00—Drugs for disorders of the urinary system
-
- A—HUMAN NECESSITIES
- A61—MEDICAL OR VETERINARY SCIENCE; HYGIENE
- A61P—SPECIFIC THERAPEUTIC ACTIVITY OF CHEMICAL COMPOUNDS OR MEDICINAL PREPARATIONS
- A61P13/00—Drugs for disorders of the urinary system
- A61P13/12—Drugs for disorders of the urinary system of the kidneys
-
- A—HUMAN NECESSITIES
- A61—MEDICAL OR VETERINARY SCIENCE; HYGIENE
- A61P—SPECIFIC THERAPEUTIC ACTIVITY OF CHEMICAL COMPOUNDS OR MEDICINAL PREPARATIONS
- A61P15/00—Drugs for genital or sexual disorders; Contraceptives
-
- A—HUMAN NECESSITIES
- A61—MEDICAL OR VETERINARY SCIENCE; HYGIENE
- A61P—SPECIFIC THERAPEUTIC ACTIVITY OF CHEMICAL COMPOUNDS OR MEDICINAL PREPARATIONS
- A61P15/00—Drugs for genital or sexual disorders; Contraceptives
- A61P15/14—Drugs for genital or sexual disorders; Contraceptives for lactation disorders, e.g. galactorrhoea
-
- A—HUMAN NECESSITIES
- A61—MEDICAL OR VETERINARY SCIENCE; HYGIENE
- A61P—SPECIFIC THERAPEUTIC ACTIVITY OF CHEMICAL COMPOUNDS OR MEDICINAL PREPARATIONS
- A61P17/00—Drugs for dermatological disorders
-
- A—HUMAN NECESSITIES
- A61—MEDICAL OR VETERINARY SCIENCE; HYGIENE
- A61P—SPECIFIC THERAPEUTIC ACTIVITY OF CHEMICAL COMPOUNDS OR MEDICINAL PREPARATIONS
- A61P19/00—Drugs for skeletal disorders
- A61P19/02—Drugs for skeletal disorders for joint disorders, e.g. arthritis, arthrosis
-
- A—HUMAN NECESSITIES
- A61—MEDICAL OR VETERINARY SCIENCE; HYGIENE
- A61P—SPECIFIC THERAPEUTIC ACTIVITY OF CHEMICAL COMPOUNDS OR MEDICINAL PREPARATIONS
- A61P19/00—Drugs for skeletal disorders
- A61P19/08—Drugs for skeletal disorders for bone diseases, e.g. rachitism, Paget's disease
-
- A—HUMAN NECESSITIES
- A61—MEDICAL OR VETERINARY SCIENCE; HYGIENE
- A61P—SPECIFIC THERAPEUTIC ACTIVITY OF CHEMICAL COMPOUNDS OR MEDICINAL PREPARATIONS
- A61P19/00—Drugs for skeletal disorders
- A61P19/08—Drugs for skeletal disorders for bone diseases, e.g. rachitism, Paget's disease
- A61P19/10—Drugs for skeletal disorders for bone diseases, e.g. rachitism, Paget's disease for osteoporosis
-
- A—HUMAN NECESSITIES
- A61—MEDICAL OR VETERINARY SCIENCE; HYGIENE
- A61P—SPECIFIC THERAPEUTIC ACTIVITY OF CHEMICAL COMPOUNDS OR MEDICINAL PREPARATIONS
- A61P21/00—Drugs for disorders of the muscular or neuromuscular system
-
- A—HUMAN NECESSITIES
- A61—MEDICAL OR VETERINARY SCIENCE; HYGIENE
- A61P—SPECIFIC THERAPEUTIC ACTIVITY OF CHEMICAL COMPOUNDS OR MEDICINAL PREPARATIONS
- A61P25/00—Drugs for disorders of the nervous system
-
- A—HUMAN NECESSITIES
- A61—MEDICAL OR VETERINARY SCIENCE; HYGIENE
- A61P—SPECIFIC THERAPEUTIC ACTIVITY OF CHEMICAL COMPOUNDS OR MEDICINAL PREPARATIONS
- A61P25/00—Drugs for disorders of the nervous system
- A61P25/02—Drugs for disorders of the nervous system for peripheral neuropathies
-
- A—HUMAN NECESSITIES
- A61—MEDICAL OR VETERINARY SCIENCE; HYGIENE
- A61P—SPECIFIC THERAPEUTIC ACTIVITY OF CHEMICAL COMPOUNDS OR MEDICINAL PREPARATIONS
- A61P25/00—Drugs for disorders of the nervous system
- A61P25/04—Centrally acting analgesics, e.g. opioids
-
- A—HUMAN NECESSITIES
- A61—MEDICAL OR VETERINARY SCIENCE; HYGIENE
- A61P—SPECIFIC THERAPEUTIC ACTIVITY OF CHEMICAL COMPOUNDS OR MEDICINAL PREPARATIONS
- A61P25/00—Drugs for disorders of the nervous system
- A61P25/06—Antimigraine agents
-
- A—HUMAN NECESSITIES
- A61—MEDICAL OR VETERINARY SCIENCE; HYGIENE
- A61P—SPECIFIC THERAPEUTIC ACTIVITY OF CHEMICAL COMPOUNDS OR MEDICINAL PREPARATIONS
- A61P25/00—Drugs for disorders of the nervous system
- A61P25/08—Antiepileptics; Anticonvulsants
-
- A—HUMAN NECESSITIES
- A61—MEDICAL OR VETERINARY SCIENCE; HYGIENE
- A61P—SPECIFIC THERAPEUTIC ACTIVITY OF CHEMICAL COMPOUNDS OR MEDICINAL PREPARATIONS
- A61P25/00—Drugs for disorders of the nervous system
- A61P25/14—Drugs for disorders of the nervous system for treating abnormal movements, e.g. chorea, dyskinesia
- A61P25/16—Anti-Parkinson drugs
-
- A—HUMAN NECESSITIES
- A61—MEDICAL OR VETERINARY SCIENCE; HYGIENE
- A61P—SPECIFIC THERAPEUTIC ACTIVITY OF CHEMICAL COMPOUNDS OR MEDICINAL PREPARATIONS
- A61P25/00—Drugs for disorders of the nervous system
- A61P25/18—Antipsychotics, i.e. neuroleptics; Drugs for mania or schizophrenia
-
- A—HUMAN NECESSITIES
- A61—MEDICAL OR VETERINARY SCIENCE; HYGIENE
- A61P—SPECIFIC THERAPEUTIC ACTIVITY OF CHEMICAL COMPOUNDS OR MEDICINAL PREPARATIONS
- A61P25/00—Drugs for disorders of the nervous system
- A61P25/20—Hypnotics; Sedatives
-
- A—HUMAN NECESSITIES
- A61—MEDICAL OR VETERINARY SCIENCE; HYGIENE
- A61P—SPECIFIC THERAPEUTIC ACTIVITY OF CHEMICAL COMPOUNDS OR MEDICINAL PREPARATIONS
- A61P25/00—Drugs for disorders of the nervous system
- A61P25/22—Anxiolytics
-
- A—HUMAN NECESSITIES
- A61—MEDICAL OR VETERINARY SCIENCE; HYGIENE
- A61P—SPECIFIC THERAPEUTIC ACTIVITY OF CHEMICAL COMPOUNDS OR MEDICINAL PREPARATIONS
- A61P25/00—Drugs for disorders of the nervous system
- A61P25/28—Drugs for disorders of the nervous system for treating neurodegenerative disorders of the central nervous system, e.g. nootropic agents, cognition enhancers, drugs for treating Alzheimer's disease or other forms of dementia
-
- A—HUMAN NECESSITIES
- A61—MEDICAL OR VETERINARY SCIENCE; HYGIENE
- A61P—SPECIFIC THERAPEUTIC ACTIVITY OF CHEMICAL COMPOUNDS OR MEDICINAL PREPARATIONS
- A61P25/00—Drugs for disorders of the nervous system
- A61P25/30—Drugs for disorders of the nervous system for treating abuse or dependence
-
- A—HUMAN NECESSITIES
- A61—MEDICAL OR VETERINARY SCIENCE; HYGIENE
- A61P—SPECIFIC THERAPEUTIC ACTIVITY OF CHEMICAL COMPOUNDS OR MEDICINAL PREPARATIONS
- A61P27/00—Drugs for disorders of the senses
- A61P27/02—Ophthalmic agents
-
- A—HUMAN NECESSITIES
- A61—MEDICAL OR VETERINARY SCIENCE; HYGIENE
- A61P—SPECIFIC THERAPEUTIC ACTIVITY OF CHEMICAL COMPOUNDS OR MEDICINAL PREPARATIONS
- A61P27/00—Drugs for disorders of the senses
- A61P27/16—Otologicals
-
- A—HUMAN NECESSITIES
- A61—MEDICAL OR VETERINARY SCIENCE; HYGIENE
- A61P—SPECIFIC THERAPEUTIC ACTIVITY OF CHEMICAL COMPOUNDS OR MEDICINAL PREPARATIONS
- A61P29/00—Non-central analgesic, antipyretic or antiinflammatory agents, e.g. antirheumatic agents; Non-steroidal antiinflammatory drugs [NSAID]
-
- A—HUMAN NECESSITIES
- A61—MEDICAL OR VETERINARY SCIENCE; HYGIENE
- A61P—SPECIFIC THERAPEUTIC ACTIVITY OF CHEMICAL COMPOUNDS OR MEDICINAL PREPARATIONS
- A61P3/00—Drugs for disorders of the metabolism
-
- A—HUMAN NECESSITIES
- A61—MEDICAL OR VETERINARY SCIENCE; HYGIENE
- A61P—SPECIFIC THERAPEUTIC ACTIVITY OF CHEMICAL COMPOUNDS OR MEDICINAL PREPARATIONS
- A61P3/00—Drugs for disorders of the metabolism
- A61P3/06—Antihyperlipidemics
-
- A—HUMAN NECESSITIES
- A61—MEDICAL OR VETERINARY SCIENCE; HYGIENE
- A61P—SPECIFIC THERAPEUTIC ACTIVITY OF CHEMICAL COMPOUNDS OR MEDICINAL PREPARATIONS
- A61P3/00—Drugs for disorders of the metabolism
- A61P3/08—Drugs for disorders of the metabolism for glucose homeostasis
- A61P3/10—Drugs for disorders of the metabolism for glucose homeostasis for hyperglycaemia, e.g. antidiabetics
-
- A—HUMAN NECESSITIES
- A61—MEDICAL OR VETERINARY SCIENCE; HYGIENE
- A61P—SPECIFIC THERAPEUTIC ACTIVITY OF CHEMICAL COMPOUNDS OR MEDICINAL PREPARATIONS
- A61P31/00—Antiinfectives, i.e. antibiotics, antiseptics, chemotherapeutics
-
- A—HUMAN NECESSITIES
- A61—MEDICAL OR VETERINARY SCIENCE; HYGIENE
- A61P—SPECIFIC THERAPEUTIC ACTIVITY OF CHEMICAL COMPOUNDS OR MEDICINAL PREPARATIONS
- A61P35/00—Antineoplastic agents
-
- A—HUMAN NECESSITIES
- A61—MEDICAL OR VETERINARY SCIENCE; HYGIENE
- A61P—SPECIFIC THERAPEUTIC ACTIVITY OF CHEMICAL COMPOUNDS OR MEDICINAL PREPARATIONS
- A61P37/00—Drugs for immunological or allergic disorders
- A61P37/02—Immunomodulators
-
- A—HUMAN NECESSITIES
- A61—MEDICAL OR VETERINARY SCIENCE; HYGIENE
- A61P—SPECIFIC THERAPEUTIC ACTIVITY OF CHEMICAL COMPOUNDS OR MEDICINAL PREPARATIONS
- A61P37/00—Drugs for immunological or allergic disorders
- A61P37/08—Antiallergic agents
-
- A—HUMAN NECESSITIES
- A61—MEDICAL OR VETERINARY SCIENCE; HYGIENE
- A61P—SPECIFIC THERAPEUTIC ACTIVITY OF CHEMICAL COMPOUNDS OR MEDICINAL PREPARATIONS
- A61P43/00—Drugs for specific purposes, not provided for in groups A61P1/00-A61P41/00
-
- A—HUMAN NECESSITIES
- A61—MEDICAL OR VETERINARY SCIENCE; HYGIENE
- A61P—SPECIFIC THERAPEUTIC ACTIVITY OF CHEMICAL COMPOUNDS OR MEDICINAL PREPARATIONS
- A61P5/00—Drugs for disorders of the endocrine system
-
- A—HUMAN NECESSITIES
- A61—MEDICAL OR VETERINARY SCIENCE; HYGIENE
- A61P—SPECIFIC THERAPEUTIC ACTIVITY OF CHEMICAL COMPOUNDS OR MEDICINAL PREPARATIONS
- A61P5/00—Drugs for disorders of the endocrine system
- A61P5/14—Drugs for disorders of the endocrine system of the thyroid hormones, e.g. T3, T4
-
- A—HUMAN NECESSITIES
- A61—MEDICAL OR VETERINARY SCIENCE; HYGIENE
- A61P—SPECIFIC THERAPEUTIC ACTIVITY OF CHEMICAL COMPOUNDS OR MEDICINAL PREPARATIONS
- A61P7/00—Drugs for disorders of the blood or the extracellular fluid
-
- A—HUMAN NECESSITIES
- A61—MEDICAL OR VETERINARY SCIENCE; HYGIENE
- A61P—SPECIFIC THERAPEUTIC ACTIVITY OF CHEMICAL COMPOUNDS OR MEDICINAL PREPARATIONS
- A61P7/00—Drugs for disorders of the blood or the extracellular fluid
- A61P7/02—Antithrombotic agents; Anticoagulants; Platelet aggregation inhibitors
-
- A—HUMAN NECESSITIES
- A61—MEDICAL OR VETERINARY SCIENCE; HYGIENE
- A61P—SPECIFIC THERAPEUTIC ACTIVITY OF CHEMICAL COMPOUNDS OR MEDICINAL PREPARATIONS
- A61P9/00—Drugs for disorders of the cardiovascular system
- A61P9/04—Inotropic agents, i.e. stimulants of cardiac contraction; Drugs for heart failure
-
- A—HUMAN NECESSITIES
- A61—MEDICAL OR VETERINARY SCIENCE; HYGIENE
- A61P—SPECIFIC THERAPEUTIC ACTIVITY OF CHEMICAL COMPOUNDS OR MEDICINAL PREPARATIONS
- A61P9/00—Drugs for disorders of the cardiovascular system
- A61P9/06—Antiarrhythmics
-
- A—HUMAN NECESSITIES
- A61—MEDICAL OR VETERINARY SCIENCE; HYGIENE
- A61P—SPECIFIC THERAPEUTIC ACTIVITY OF CHEMICAL COMPOUNDS OR MEDICINAL PREPARATIONS
- A61P9/00—Drugs for disorders of the cardiovascular system
- A61P9/10—Drugs for disorders of the cardiovascular system for treating ischaemic or atherosclerotic diseases, e.g. antianginal drugs, coronary vasodilators, drugs for myocardial infarction, retinopathy, cerebrovascula insufficiency, renal arteriosclerosis
-
- A—HUMAN NECESSITIES
- A61—MEDICAL OR VETERINARY SCIENCE; HYGIENE
- A61P—SPECIFIC THERAPEUTIC ACTIVITY OF CHEMICAL COMPOUNDS OR MEDICINAL PREPARATIONS
- A61P9/00—Drugs for disorders of the cardiovascular system
- A61P9/12—Antihypertensives
-
- G—PHYSICS
- G16—INFORMATION AND COMMUNICATION TECHNOLOGY [ICT] SPECIALLY ADAPTED FOR SPECIFIC APPLICATION FIELDS
- G16C—COMPUTATIONAL CHEMISTRY; CHEMOINFORMATICS; COMPUTATIONAL MATERIALS SCIENCE
- G16C20/00—Chemoinformatics, i.e. ICT specially adapted for the handling of physicochemical or structural data of chemical particles, elements, compounds or mixtures
- G16C20/50—Molecular design, e.g. of drugs
-
- G—PHYSICS
- G16—INFORMATION AND COMMUNICATION TECHNOLOGY [ICT] SPECIALLY ADAPTED FOR SPECIFIC APPLICATION FIELDS
- G16C—COMPUTATIONAL CHEMISTRY; CHEMOINFORMATICS; COMPUTATIONAL MATERIALS SCIENCE
- G16C99/00—Subject matter not provided for in other groups of this subclass
-
- G—PHYSICS
- G16—INFORMATION AND COMMUNICATION TECHNOLOGY [ICT] SPECIALLY ADAPTED FOR SPECIFIC APPLICATION FIELDS
- G16H—HEALTHCARE INFORMATICS, i.e. INFORMATION AND COMMUNICATION TECHNOLOGY [ICT] SPECIALLY ADAPTED FOR THE HANDLING OR PROCESSING OF MEDICAL OR HEALTHCARE DATA
- G16H20/00—ICT specially adapted for therapies or health-improving plans, e.g. for handling prescriptions, for steering therapy or for monitoring patient compliance
- G16H20/10—ICT specially adapted for therapies or health-improving plans, e.g. for handling prescriptions, for steering therapy or for monitoring patient compliance relating to drugs or medications, e.g. for ensuring correct administration to patients
-
- A—HUMAN NECESSITIES
- A61—MEDICAL OR VETERINARY SCIENCE; HYGIENE
- A61K—PREPARATIONS FOR MEDICAL, DENTAL OR TOILETRY PURPOSES
- A61K2300/00—Mixtures or combinations of active ingredients, wherein at least one active ingredient is fully defined in groups A61K31/00 - A61K41/00
Definitions
- ADRs adverse drug reactions
- a drug's efficacy against disases is a fundamental issue.
- side effects or "adverse drug reactions” (“ADRs") caused by a drug can profoundly impact the patient, thus requiring alterations in the treatment plan.
- ADRs account for -7% of all hospitalizations and consistently rank as one of the most common causes of inpatient death in western countries.
- ADRs non-steroidal ant i -i nfl ammatory drugs
- Cyclooxygenase-2 inhibitors is there an association with coronary or renal events?, Current Atherosclerosis Reports 2003;5:1 14-7.)
- FIG. 1 is a scatterplot graph from McAdams et al. displaying the relationship between LPS-stimulated plasma PGE2 ex vivo, an index of COX-2 activity, and log plasma concentrations of celecoxib at 2, 4, 6, and 24 hours after dosing. PGE2 is expressed as a percentage of predosing values. A variable dose-response is evident. (P , 0.01 vs. placebo).
- ⁇ Scale ranged from 1 (very good) to 5 (very poor).
- Patient improvement was defined as a reduction of at least 2 grades from baseline for grades 3 through 5 or a change in grade from 2 tl .
- Patient worsening was defined as an increase of at least 2 grades from baseline for grades ⁇ through 3, or a change in grade from 4 to 5.
- t P ⁇ .05 vs placebo;
- ⁇ [] Scale ranged from 0 to 24 with negative change indicating improvement;
- # P ⁇ .05 vs naproxen
- the Celebrex® dosage prescribed for the treatment of osteoarthritis is standardized (e.g., 50, 100, 200 or 400 mg dosage forms) regardless of the gender and age of the patient receiving celecoxib.
- studies have shown that, on average, elderly patients receiving 100 mg celecoxib doses over a six week period reported almost identical reductions in pain as compared to patients receiving 200 mg celecoxib doses over a six week period.
- the subjects receiving the 100 nig dose of celecoxib also reported fewer side effects for the duration of the study.
- the results indicate that patients may experience the same celecoxib efficacy at lower, safer doses. Accordingly, there is a need for improved methods of using NSAIDs in the therapy of arthritic pain.
- the present invention addresses the the wide variability in the responses individuals have to the same dosage of a drug by setting forth methods for individualizing drug therapy.
- the methods of the present invention individualize dosages a patient takes, thus maximizing the efficacy of one or more drugs at the lowest doses possible and at the point of care.
- the present invention can increase drug compliance, reduce costs, and most importantly improve the quality and safety of patient lives.
- the invention provides methods for individualized therapy of arthritic pain using a non-steroidal anti-inflammatory drug (NSAID).
- NSAID non-steroidal anti-inflammatory drug
- the high patient to patient variability in response to a dose of any NSAID makes the mere clinical monitoring of patients an inadequate way to treat patients with this class of drugs. Even the measurement of "blood levels'” (i.e., the ocasional measurement of the drug's concentration in the blood) is unlikely to lead to effective nontoxic regimens.
- blood levels' i.e., the ocasional measurement of the drug's concentration in the blood
- a more compressive set of metrics must employed in each patient.
- the methods claimed herein take advantage of a pharmacokinetic ("PK") analysis for each patient. As such, the claimed methods go beyond the measurement of a single blood level at a single time point.
- PK pharmacokinetic
- the claimed methods make use of data from several time points and take advantage of the full scope of PK parameters.
- the claimed method seeks to determined the individual PK directly.
- the inventive methods disclosed herein comprise: administering to a first patient suffering from arthritic pain a first NSAID formulation; determining the NSAID 's concentration in the first patient's blood at a plurality of time points after the first NSAID formulation was administered to the first patient; transforming the first patient's NSAID concentration/time data points in to one or more PK parameters; comparing the first patient's values for said PK parameters to a predetermined ranges of values for each PK parameter and if one or more of the first patient's PK parameters fall outside o a predetermined range, designing a new NSAID formulation, wherein the dose of said NSAID can be different from that of the first NSAID formulation.
- the types and amounts of excipients can also differ from those of the first NSAID formulation, or both.
- the new NSAID formulation is then administered to the first patient and the steps used to determine the PK parameters are repeated until all the PK parameters used are within said predetermined ranges, and if pain control is adequate and toxicity is tolerable, maintaining the first patient on the NSAID formulation at frequency of administration that satisfied the comparison within predetermined ranges.
- FIG. 1 is a scatterplot graph displaying the relationship between LPS-stimulated plasma PGE2 ex vivo, an index of COX-2 activity, and log plasma concentrations of celecoxib 2, 4, 6, and 24 hours after dosing.
- PGE2 is expressed as a percentage of predosing values. A steep but variable dose-response is evident. (P , 0.01 vs. placebo) (from McAdam et al. Systemic biosynthesis of prostacyclin by cyclooxygenase (COX)-2: the human pharmacology of a selective inhibitor of COX-2. PNAS. 1999; 96:272-7.)
- FIG. 3 displays the result of a meta-analysis of the one dose AUC from patients in different age groups.
- individualized therapy refers to a specific treatment regimen for a patient comprising the administration of one or more drugs, which is the result of analyzing pharmacokinetic and/or pharmacodynamic parameters of the subject to maximize drug efficacy at about the lowest dosage of the drug(s) possible.
- arthritic pain refers to any pain arising anatomically from the joints and their adjacent bones and non-osseous tissues. Any arthritic pain can be treated by the invention including, without limitation, any pain resulting from an auto-immune, infectious, inflammatory, proliferative, regenerative or degenerative process so involving the joints of an animal or human patient. As such, suitable pain treatable with the current invention includes pain from rheumatoid or osteo arthritis.
- formulation refers to a combination of active ingredients and excipients wherein each is present in a dosage form at fixed ratios to one another (i.e., fixed percentages of each ingrediant in the dosage form.)
- first NSAID formulation is the NSAID formulation that is administered to the patient to begin the process by which PK parameters are determined and "new NSAID formulation” is the formulation designed based on the PK parameters produced by the first NSAID formulation.
- new NSAID formulation is the formulation designed based on the PK parameters produced by the first NSAID formulation.
- the new NSAID formulation may be a second formulation.
- second formulation and “second formulation under a second drug regimen” refer to the dosage of one or more drugs an individual receives after performing certain steps of the claimed invention (e.g., after comparing an patient's pharmacokinetic parameters to a predetermined range of values).
- the second formulation under a second regimen can be, e.g., the same dosage of a drug administered in the first regimen, a lower dose, or a higher dose.
- first formulation under a first regimen and “first formulation” refer to the dosage of one or more drugs an individual initially receives prior to performing one or more steps of the claimed invention.
- the first formulation under a first regimen can be, e.g., the standard 100 mg or 200 mg dosages of celecoxib prescribed to patients over 60 kg twice daily for osteoarthritis.
- NSAID concentration/time data points refers to the amount of NSAID in a unit of volume (e.g., 1 ml of blood from a subject) at a given point in time before or after administration of the NSAID.
- the phrase "predetermined range of values” refers to a known range of values (e.g., pharmacokinetic parameters) associated with desirable drug efficacy at lower risk doses of a drug (e.g., the C max range corresponding to patients experiencing high drug efficacy at a low dose).
- the predetermined range of values may be derived from a statistical analysis of a population receiving variable and/or identical doses of one or more drugs.
- the predetermined range of values can readily be compared to a patient's values (e.g., pharmacokinetic values), associated with one or more drugs.
- the predetermined ranges are determined (i.e. derived) from other patients for whom there was improved pain levels without significant side effects.
- Signal side effects refer to side effects that the patient finds intolerable, impair physiologic functions, and/or put the patient at risk for immobility and/or death or combinations thereof.
- designing refers to changes in the active agent's dose, formulation and/or regiment based on the patient data, using logic and the experience of one of ordinary skill in the art.
- determining the level of efficacy refers to the use of objective (e.g., pharmacokinetic) and subjective tests (e.g., pharmacodynamic), signs and symptoms to characterize, quantify or evaluate how well symptoms (e.g., pain) are controlled by the administration of the active ingredient (e.g., celecoxib).
- objective e.g., pharmacokinetic
- subjective tests e.g., pharmacodynamic
- signs and symptoms e.g., pharmacodynamic
- determining the level of toxicity refers to the use of objective and subjective tests, signs and symptoms to characterize, quantify or evaluate the significance of any side effects produced by the administration of the active ingredient.
- pain control is adequate refers to a level of pain the patient is willing to live with and does not significantly impair the patient's functioning in society or the patient's physiologic functions.
- toxicity is acceptable refers to the absence of significant side effects and a level of toxicity that the patient is willing to live with and does not significantly impair the patient's functioning in society or the patient's physiologic functions.
- a "COX-2 inhibitor” refers to a non-steroidal anti-inflammatory drug that is capable of directly targeting the COX-2 enzyme in a subject and inhibits at least some COX-1 activity, e.g., celecoxib.
- a "mixed COX-1 and COX-2 inhibitor” refers to a non-steroidal anli -i nflammato ry drug that is capable of directly targeting both the COX-1 and COX-2 enzymes in a subject and inhibits at least some COX- 1 and COX-2 activity, e.g., ibuprofen.
- a mixed COX-2 inhibitor can also include a COX-2 inhibitor such as celecoxib combined with one or more other therapeutic drugs for chronic diseases such as arthritis, diabetes, hypertension, hypercholesterolemia, and dementia.
- Suitable therapeutic drugs may include, but are not limited to: aspirin, diclofenac (Cataflam, Voltaren), diflusnisal (Dolobid), etodolac (Lodine), fenoprofen (Nalfon), flubiprofen (Ansaid), ibuprofen (Motrin, Advil, Nuprin), indomethacin (Indocin), ketoprofen (Orudis), ketorolac (Toradol), meclofenamate, nabumetone (Relafen), naproxen (Naprosyn), oxaprozin (Daypro), phenylbutazone, piroxicam (Feldene), salicylate, sulindac (Clinor
- hydrocortisone methylprednisolone, prednisolone, prednisone, triamcinolone, sulfonylureas, acetohexamide (Dymelor), chlorpropamide (Diabinese), glimepiride (Amaryl), glipizide (Glucotrol), glyburide (Micronase, DiaBeta), tolazamide (Tolinase), tolbutamide (Orinase), Biguanides, metformin (Glucophage), Alpha-glucosidase Inhibitors, acarbose (Precose), miglitol (Glyset), Thiazolidinedione Derivatives, pioglitazone (Actos), rosiglitazone
- the combination can also include a "fixed dose combination” (FDC) or simply dosing with multiple pills each of a single agent to achieve a desired effect.
- FDC fixed dose combination
- the invention provides methods for individualized therapy of arthritic pain using a non-steroidal anti-inflammatory drug (NSAID), preferably celecoxib.
- NSAID non-steroidal anti-inflammatory drug
- the invention provides methods for predicting the outcome of the therapy arthritic pain with a composition comprising NSAID, preferably celecoxib.
- the invention provides methods of using a NSAID, including aspirin, preferably celecoxib, in the manufacture of medicament for the treatment of arthritic pain.
- This disclosure provides processes in accordance with invention comprising: administering a first formulation under a first regimen comprising a NSAID, preferably celecoxib, at a first dose to a patient suffering from arthritic pain; at a pre-specified time or times after administration of the first dose o the NSAID, measuring the NSAID' s concentration in the patient's blood (e.g., by a point of care device, or by other suitable techniques known in the art) at a plurality of time points after administering the first formulation resulting in a set of NSAID concentration/time data points; transforming the patient's NSAID concentration/time data points in to one or more pharmacokinetic (PK) parameters; comparing the patient's PK parameters to a predetermined ranges of values for such PK parameters and if one or more of the PK parameters fall outside of the PK
- NSAID preferably celecoxib
- the invention further provides methods for individualized drug therapy of arthritic pain with a NSAID, preferably celecoxib, comprising: administering a NSAID at a first dose under a first regimen to a patient suffering from arthritic pain; determining the concentration of the NSAID at a plurality of pre-specified time points after administration of the first dose of the NSAID; using the concentration/time data, deriving one or more pharmacokinetic (PK) parameters exhibited by the NSAID when administered to said patient; determining the level of efficacy and toxicity produced by the first dose and regiment; using the level of efficacy and toxicity produced by said first dose to determine a new dose of the NSAID;
- PK pharmacokinetic
- any suitable NSAID can be used in accordance with the invention, including without limitation, a COX- 1 -specific inhibitor, a COX-2-specific inhibitor, a mixed COX-1 and 2 inhibitor or a combination thereof.
- the NSAID can be a salicylate, propionic acid derivative, acetic acid derivative, enolic acid (oxicam) derivative, anthranilic acid derivative (fenamatea ) or combinations thereof.
- the NSAID can be, aspirin (acetylsalicylic acid), ibuprofen, naproxen, indomethacin, sulindac, piroxicam, clonixin, preferably celecoxib or a combination thereof.
- the invention can be used with combinations of NSAIDs and other analgesic drugs such as lidocaine, opiates, acetaminophen, tricylic antidepressants, anticonvulsants, carbamazepine, gabapentin, and pregabalin; other anti- inflammatory drugs such as steroids and immunosuppressants.
- NSAIDs and other therapies for arthritis including but not limited to, methotrexate and gold-salts.
- the NSAID can be administered in accordance with the invention via any suitable route including, without limiting, orally, rectally, by inhalation, trans-cutaneously, by injection, intra-venously or intra-arterially.
- the non-NSAID component of any combination therapy can be administered in accordance with the invention by any suitable route including, without limiting, orally, rectally, by inhalation, trans-cutaneously, by injection, intravenously or intra-arterially.
- Any suitable regimen can be used in accordance with the invention to administer two or more drug components, including without limitation, simultaneously (within minutes of one another), substantially simultaneously (within an hour of one another) or at different times.
- NSAID drug therapy e.g., a celecoxib therapy
- a prescribed cholesterol regulator such as atorvastatin
- Any suitable PK parameter or parameters can be used in accordance with the invention, including without limiting concentration, concentration time course, peak concentration, and time after administration to peak concentration, terminal half-life, AUC, bioavailability, absorption, distribution, metabolism, excretion, biotransformation, or a combination thereof.
- any suitable method for the assessment of pain known to those of ordinary skill in the art can be used in accordnce with the invention, including, but not limited to, one- dimensional pain intensity scales, Wisconsin Brief Pain Questionnaire, Brief Pain Inventory, The McGill Pain Questionnaire and the short-form, McGill Pain Questionnaire (See Breivik et al: Assessment of pain, British Journal of Anaesthesia 2008, 101 (1): 17-24).
- the following examples further illustrate the invention but, of course, should not be construed as in any way limiting its scope.
- the approved prescribing information for Celebrex® as listed on its package insert for US/EU/ROW instructs that a physician should use lowest effective dose for the shortest duration consistent with treatment goals for the individual patient.
- the package insert includes a 100 mg BID regimen:
- Rheumatoid Arthritis 100 mg BID or 200 mg BID
- JRA Juvenile Rheumatoid Arthritis
- Ankylosing Spondylitis 200 mg once daily single dose or 100 mg BID.
- AP Acute Pain
- PD Primary Dysmenorrhea
Landscapes
- Health & Medical Sciences (AREA)
- Chemical & Material Sciences (AREA)
- General Health & Medical Sciences (AREA)
- Medicinal Chemistry (AREA)
- Life Sciences & Earth Sciences (AREA)
- Pharmacology & Pharmacy (AREA)
- Public Health (AREA)
- Engineering & Computer Science (AREA)
- Veterinary Medicine (AREA)
- Animal Behavior & Ethology (AREA)
- Bioinformatics & Cheminformatics (AREA)
- Organic Chemistry (AREA)
- Nuclear Medicine, Radiotherapy & Molecular Imaging (AREA)
- General Chemical & Material Sciences (AREA)
- Chemical Kinetics & Catalysis (AREA)
- Epidemiology (AREA)
- Neurology (AREA)
- Biomedical Technology (AREA)
- Neurosurgery (AREA)
- Diabetes (AREA)
- Physical Education & Sports Medicine (AREA)
- Orthopedic Medicine & Surgery (AREA)
- Rheumatology (AREA)
- Immunology (AREA)
- Cardiology (AREA)
- Endocrinology (AREA)
- Hematology (AREA)
- Pain & Pain Management (AREA)
- Theoretical Computer Science (AREA)
- Bioinformatics & Computational Biology (AREA)
- Computing Systems (AREA)
- Heart & Thoracic Surgery (AREA)
- Physics & Mathematics (AREA)
- Crystallography & Structural Chemistry (AREA)
- Pulmonology (AREA)
- Psychiatry (AREA)
- Spectroscopy & Molecular Physics (AREA)
- Urology & Nephrology (AREA)
- Obesity (AREA)
- Primary Health Care (AREA)
Abstract
Description


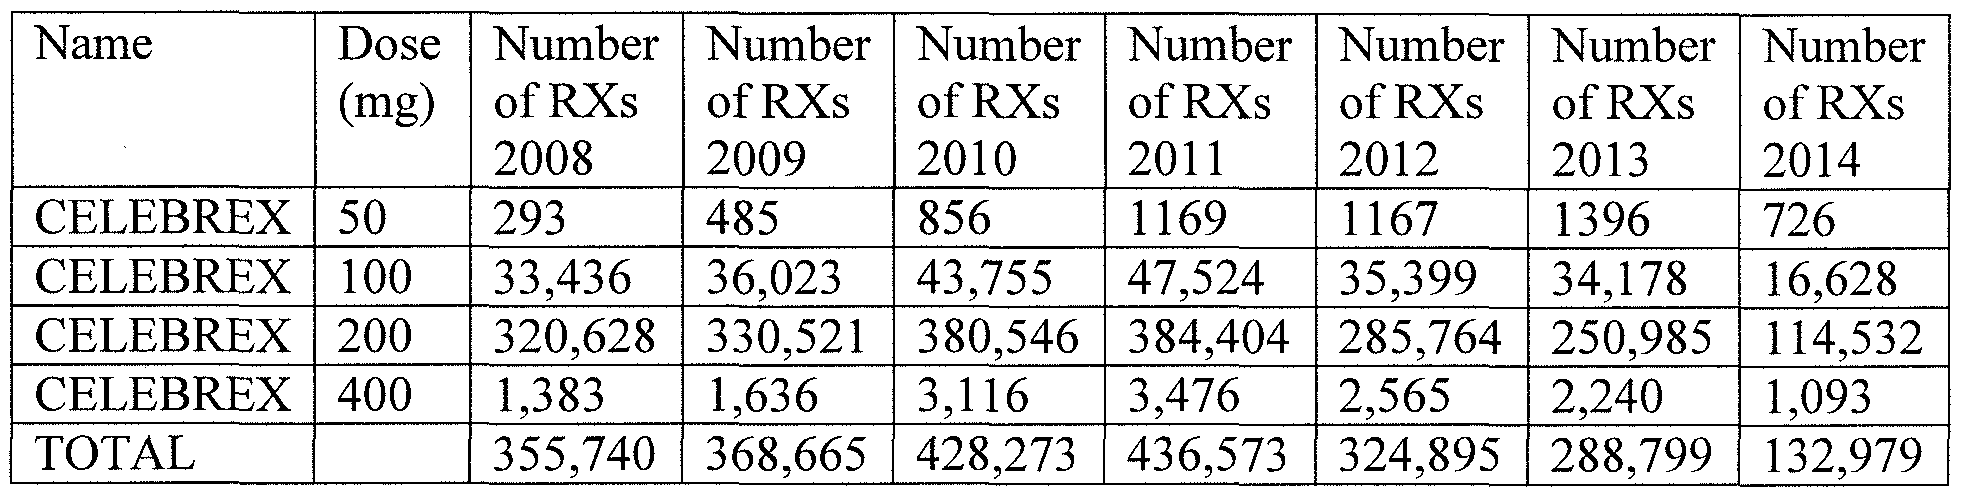
Claims
Priority Applications (34)
| Application Number | Priority Date | Filing Date | Title |
|---|---|---|---|
| KR1020157034125A KR20160098029A (en) | 2015-01-13 | 2015-01-13 | Method for individualized drug therapy |
| EP15878203.7A EP3245602A4 (en) | 2015-01-13 | 2015-01-13 | Method for individualized drug therapy |
| AU2015377253A AU2015377253A1 (en) | 2015-01-13 | 2015-01-13 | Method for individualized drug therapy |
| JP2017536310A JP2018508476A (en) | 2015-01-13 | 2015-01-13 | Methods for personalized drug therapy |
| CN201580077772.8A CN107408147A (en) | 2015-01-13 | 2015-01-13 | Method for Individual drug treatment |
| CA2973569A CA2973569A1 (en) | 2015-01-13 | 2015-01-13 | Method for individualized drug therapy |
| PCT/US2015/011148 WO2016114761A1 (en) | 2015-01-13 | 2015-01-13 | Method for individualized drug therapy |
| CA2956899A CA2956899A1 (en) | 2014-06-08 | 2015-06-08 | Fixed dose combination for pain relief without edema |
| EP15806490.7A EP3151822A4 (en) | 2014-06-08 | 2015-06-08 | Fixed dose combination for pain relief without edema |
| AU2015274895A AU2015274895A1 (en) | 2014-06-08 | 2015-06-08 | Fixed dose combination for pain relief without edema |
| PCT/US2015/034706 WO2015191460A1 (en) | 2014-06-08 | 2015-06-08 | Fixed dose combination for pain relief without edema |
| CN201580040734.5A CN106572984A (en) | 2014-06-08 | 2015-06-08 | Fixed dose combination for pain relief without causing edema |
| JP2016571720A JP2017517529A (en) | 2014-06-08 | 2015-06-08 | Combination of fixed doses to reduce pain without edema |
| EP15807276.9A EP3151823A4 (en) | 2014-06-08 | 2015-06-08 | Fixed dose combination for pain relief without edema |
| CN201580042156.9A CN106572985A (en) | 2014-06-08 | 2015-06-08 | Fixed dose combination for pain relief without edema |
| KR1020167015176A KR20160091349A (en) | 2014-06-08 | 2015-06-08 | Fixed dose combination for pain relief without edema |
| AU2015274908A AU2015274908A1 (en) | 2014-06-08 | 2015-06-08 | Fixed dose combination for pain relief without edema |
| PCT/US2015/034738 WO2015191473A1 (en) | 2014-06-08 | 2015-06-08 | Fixed dose combination for pain relief without edema |
| KR1020167015173A KR20160091348A (en) | 2014-06-08 | 2015-06-08 | Fixed dose combination for pain relief without edema |
| JP2017516649A JP2017517575A (en) | 2014-06-08 | 2015-06-08 | Fixed dose combination to reduce pain without edema |
| CA2956897A CA2956897A1 (en) | 2014-06-08 | 2015-06-08 | Fixed dose combination for pain relief without edema |
| US14/798,737 US20160022639A1 (en) | 2014-07-14 | 2015-07-14 | Fixed dose combination for pain relief without edema |
| US14/798,753 US20160008371A1 (en) | 2014-07-14 | 2015-07-14 | Fixed dose combination for pain relief without edema |
| TW104142786A TW201625307A (en) | 2015-01-13 | 2015-12-18 | Method for individualized drug therapy |
| PCT/US2016/012914 WO2016115057A1 (en) | 2015-01-13 | 2016-01-11 | Fixed dose combination for pain relief without edema |
| US14/993,037 US20160120885A1 (en) | 2014-07-14 | 2016-01-11 | Fixed dose combination for pain relief without edema |
| TW105109708A TW201642906A (en) | 2014-06-08 | 2016-03-28 | Fixed dose combination for pain relief without edema |
| TW105109706A TW201642854A (en) | 2014-06-08 | 2016-03-28 | Fixed dose combination for pain relief without edema |
| US15/298,222 US20170035787A1 (en) | 2014-07-14 | 2016-10-19 | Fixed Dose Combination for Pain Relief Without Edema |
| US15/360,971 US20170071956A1 (en) | 2014-07-14 | 2016-11-23 | Fixed Dose Combination for Pain Relief Without Edema |
| US15/490,883 US20170326109A1 (en) | 2014-07-14 | 2017-04-18 | Fixed Dose Combination for Pain Relief Without Edema |
| US16/173,924 US20190125727A1 (en) | 2014-07-14 | 2018-10-29 | Fixed dose combination for pain relief without edema |
| US16/183,638 US20190070201A1 (en) | 2014-07-14 | 2018-11-07 | Fixed dose combination for pain relief without edema |
| US16/206,953 US20190091243A1 (en) | 2014-07-14 | 2018-11-30 | Fixed dose combination for pain relief without edema |
Applications Claiming Priority (1)
| Application Number | Priority Date | Filing Date | Title |
|---|---|---|---|
| PCT/US2015/011148 WO2016114761A1 (en) | 2015-01-13 | 2015-01-13 | Method for individualized drug therapy |
Related Parent Applications (2)
| Application Number | Title | Priority Date | Filing Date |
|---|---|---|---|
| PCT/US2015/034706 Continuation-In-Part WO2015191460A1 (en) | 2014-06-08 | 2015-06-08 | Fixed dose combination for pain relief without edema |
| PCT/US2015/034738 Continuation-In-Part WO2015191473A1 (en) | 2014-06-08 | 2015-06-08 | Fixed dose combination for pain relief without edema |
Related Child Applications (4)
| Application Number | Title | Priority Date | Filing Date |
|---|---|---|---|
| PCT/US2015/034738 Continuation-In-Part WO2015191473A1 (en) | 2014-06-08 | 2015-06-08 | Fixed dose combination for pain relief without edema |
| US14/798,737 Continuation-In-Part US20160022639A1 (en) | 2014-07-14 | 2015-07-14 | Fixed dose combination for pain relief without edema |
| US14/798,753 Continuation-In-Part US20160008371A1 (en) | 2014-07-14 | 2015-07-14 | Fixed dose combination for pain relief without edema |
| US14/993,037 Continuation-In-Part US20160120885A1 (en) | 2014-07-14 | 2016-01-11 | Fixed dose combination for pain relief without edema |
Publications (1)
| Publication Number | Publication Date |
|---|---|
| WO2016114761A1 true WO2016114761A1 (en) | 2016-07-21 |
Family
ID=56406160
Family Applications (1)
| Application Number | Title | Priority Date | Filing Date |
|---|---|---|---|
| PCT/US2015/011148 Ceased WO2016114761A1 (en) | 2014-06-08 | 2015-01-13 | Method for individualized drug therapy |
Country Status (7)
| Country | Link |
|---|---|
| EP (1) | EP3245602A4 (en) |
| JP (1) | JP2018508476A (en) |
| KR (1) | KR20160098029A (en) |
| CN (1) | CN107408147A (en) |
| AU (1) | AU2015377253A1 (en) |
| CA (1) | CA2973569A1 (en) |
| WO (1) | WO2016114761A1 (en) |
Cited By (2)
| Publication number | Priority date | Publication date | Assignee | Title |
|---|---|---|---|---|
| EP4267132A1 (en) * | 2020-12-28 | 2023-11-01 | Dr. Reddy's Laboratories Ltd. | Celecoxib for treating pain |
| US12546762B2 (en) | 2018-06-07 | 2026-02-10 | Raysearch Laboratories Ab (Publ) | Method and system for evaluation of drug concentration in blood, plasma or serum |
Families Citing this family (2)
| Publication number | Priority date | Publication date | Assignee | Title |
|---|---|---|---|---|
| EP3792932A1 (en) * | 2019-09-13 | 2021-03-17 | Hill-Rom Services, Inc. | Personalized vital sign monitors |
| CN116999560A (en) * | 2022-04-30 | 2023-11-07 | 武汉思瓴生物科技有限公司 | Drug combinations that can treat pain and their applications |
Citations (3)
| Publication number | Priority date | Publication date | Assignee | Title |
|---|---|---|---|---|
| US20060078621A1 (en) * | 2004-10-13 | 2006-04-13 | Wedinger Robert S | Method of providing customized drug delivery systems |
| US20070202170A1 (en) * | 1999-12-22 | 2007-08-30 | Pharmacia Corporation | Dual-release compositions of a cyclooxygenase-2 inhibitor |
| WO2012166795A1 (en) * | 2011-05-30 | 2012-12-06 | String Therapeutics Inc. | Methods and compositions for therapeutic drug monitoring and dosing by point-of-care pharmacokinetic profiling |
Family Cites Families (1)
| Publication number | Priority date | Publication date | Assignee | Title |
|---|---|---|---|---|
| UA74539C2 (en) * | 1999-12-08 | 2006-01-16 | Pharmacia Corp | Crystalline polymorphous forms of celecoxib (variants), a method for the preparation thereof (variants), a pharmaceutical composition (variants) |
-
2015
- 2015-01-13 KR KR1020157034125A patent/KR20160098029A/en not_active Ceased
- 2015-01-13 EP EP15878203.7A patent/EP3245602A4/en not_active Withdrawn
- 2015-01-13 JP JP2017536310A patent/JP2018508476A/en active Pending
- 2015-01-13 CA CA2973569A patent/CA2973569A1/en not_active Abandoned
- 2015-01-13 CN CN201580077772.8A patent/CN107408147A/en active Pending
- 2015-01-13 AU AU2015377253A patent/AU2015377253A1/en not_active Abandoned
- 2015-01-13 WO PCT/US2015/011148 patent/WO2016114761A1/en not_active Ceased
Patent Citations (3)
| Publication number | Priority date | Publication date | Assignee | Title |
|---|---|---|---|---|
| US20070202170A1 (en) * | 1999-12-22 | 2007-08-30 | Pharmacia Corporation | Dual-release compositions of a cyclooxygenase-2 inhibitor |
| US20060078621A1 (en) * | 2004-10-13 | 2006-04-13 | Wedinger Robert S | Method of providing customized drug delivery systems |
| WO2012166795A1 (en) * | 2011-05-30 | 2012-12-06 | String Therapeutics Inc. | Methods and compositions for therapeutic drug monitoring and dosing by point-of-care pharmacokinetic profiling |
Non-Patent Citations (1)
| Title |
|---|
| See also references of EP3245602A4 * |
Cited By (2)
| Publication number | Priority date | Publication date | Assignee | Title |
|---|---|---|---|---|
| US12546762B2 (en) | 2018-06-07 | 2026-02-10 | Raysearch Laboratories Ab (Publ) | Method and system for evaluation of drug concentration in blood, plasma or serum |
| EP4267132A1 (en) * | 2020-12-28 | 2023-11-01 | Dr. Reddy's Laboratories Ltd. | Celecoxib for treating pain |
Also Published As
| Publication number | Publication date |
|---|---|
| CN107408147A (en) | 2017-11-28 |
| AU2015377253A1 (en) | 2017-08-31 |
| EP3245602A4 (en) | 2018-09-05 |
| EP3245602A1 (en) | 2017-11-22 |
| CA2973569A1 (en) | 2016-07-21 |
| KR20160098029A (en) | 2016-08-18 |
| JP2018508476A (en) | 2018-03-29 |
Similar Documents
| Publication | Publication Date | Title |
|---|---|---|
| Portenoy | Treatment of cancer pain | |
| Pahwa et al. | Impact of dyskinesia on activities of daily living in Parkinson's disease: results from pooled phase 3 ADS-5102 clinical trials | |
| Saengnipanthkul et al. | Differentiation of patented crystalline glucosamine sulfate from other glucosamine preparations will optimize osteoarthritis treatment | |
| EP3245602A1 (en) | Method for individualized drug therapy | |
| Toth | Drug safety evaluation of pregabalin | |
| US20190091243A1 (en) | Fixed dose combination for pain relief without edema | |
| Tolman et al. | Vigabatrin: a comprehensive review of drug properties including clinical updates following recent FDA approval | |
| US20160199392A1 (en) | Method for individualized drug therapy | |
| Poudel et al. | Irrational fixed dose combinations in Nepal: need for intervention | |
| Manvelian et al. | A phase I study evaluating the pharmacokinetic profile of a novel, proprietary, nano-formulated, lower-dose oral indomethacin | |
| Hwang et al. | Gabapentin versus Transdermal Fentanyl Matrix for the Alleviation of Chronic Neuropathic Pain of Radicular Origin: A Randomized Blind Multicentered Parallel‐Group Noninferiority Trial | |
| Pergolizzi Jr et al. | The potential role of an extended-release, abuse-deterrent oxycodone/acetaminophen fixed-dose combination product for the treatment of acute pain | |
| Muranova et al. | Levodopa/carbidopa/entacapone combination therapy | |
| Hershey et al. | Treatment of pediatric and adolescent migraine | |
| Şermet et al. | Analgesic prescription pattern in the management of dental pain among dentists in İstanbul | |
| TW201625307A (en) | Method for individualized drug therapy | |
| Hollenack et al. | The application of evidence-based principles of care in older persons (issue 4): pain management | |
| Siddalingaiah et al. | Evergreened drugs or evergreened profits? | |
| JP2017517529A (en) | Combination of fixed doses to reduce pain without edema | |
| Ohta et al. | Rotigotine transdermal patch does not make Parkinson disease patients sleepy during daytime | |
| Clark et al. | Pharmacological management of orofacial pain–a clinician’s guide | |
| Stocchi et al. | An evaluation of the efficacy and value of CVT-301 for the treatment of Parkinson’s disease | |
| Naraharisetti et al. | Effects of food on bioavailability of analgesics; resulting dosage and administration recommendations | |
| Ravichandran et al. | Knowledge, attitude and prescriptional practice about fixed dose combinations among medical practitioners in Tertiary care hospital | |
| Prasetyo et al. | Effectiveness of Stalevo Drug Usage in Parkinson's Patients: A Narrative Review |
Legal Events
| Date | Code | Title | Description |
|---|---|---|---|
| ENP | Entry into the national phase |
Ref document number: 20157034125 Country of ref document: KR Kind code of ref document: A |
|
| 121 | Ep: the epo has been informed by wipo that ep was designated in this application |
Ref document number: 15878203 Country of ref document: EP Kind code of ref document: A1 |
|
| ENP | Entry into the national phase |
Ref document number: 2017536310 Country of ref document: JP Kind code of ref document: A |
|
| ENP | Entry into the national phase |
Ref document number: 2973569 Country of ref document: CA |
|
| NENP | Non-entry into the national phase |
Ref country code: DE |
|
| REEP | Request for entry into the european phase |
Ref document number: 2015878203 Country of ref document: EP |
|
| ENP | Entry into the national phase |
Ref document number: 2015377253 Country of ref document: AU Date of ref document: 20150113 Kind code of ref document: A |